

Gene therapy goes after the faulty instructions behind a disease, not just its symptoms. Here is how it works, what is approved, what it costs and where AI fits in.
At a glance: Gene therapy treats a disease by changing the genes inside a patient’s cells: adding a working copy, switching off a harmful one, or editing the faulty spelling. The new instructions usually travel inside an emptied-out virus called a vector, most often AAV or a lentivirus. Landmarks include Luxturna (2017), Zolgensma (2019) and Casgevy, the first CRISPR medicine (2023), plus at least four FDA approvals in 2026. Several cost $2 million or more and carry real risks. AI now helps design better vectors.
Not medical advice. This page explains how AI is being used in medicine; it can’t tell you what’s right for your health, so talk to a doctor or pharmacist about your own care. Facts checked against the linked sources on October 29, 2026. How we research and check our guides.
What is gene therapy?
Every cell in your body carries genes, which are instructions for building proteins. When one instruction has a typo, the protein comes out broken or missing, and that can cause disease. Gene therapy goes after the instruction itself. The US National Human Genome Research Institute puts it simply: it is “a technique that uses a gene(s) to treat, prevent or cure a disease” (NHGRI).

Most medicines are taken again and again. Many gene therapies are given once: if the cell gets a working instruction, it can keep making the right protein on its own for years.
Words you will meet
- Gene
- A stretch of DNA that tells a cell how to make one protein.
- Vector
- The delivery vehicle that carries new genetic instructions into cells. Usually a virus with its harmful parts removed.
- Capsid
- The protein shell of a virus. It decides which cells the vector can get into.
- Promoter
- A short “on switch” placed in front of a gene. It controls which cells read it.
- CRISPR
- A tool that cuts DNA at a chosen spot so the gene there can be changed.
Three ways to change a gene
The FDA describes the main approaches. In everyday terms they come down to three jobs:
- Add a working copy. The faulty gene stays, but the cell gets a correct backup to read. Luxturna and Zolgensma work this way.
- Switch a harmful gene off. Some diseases come from a gene doing too much. A therapy can deliver instructions that quiet it down.
- Edit the gene itself. Tools like CRISPR cut or rewrite the DNA in place. Casgevy, the first CRISPR-based medicine, edits a patient’s blood stem cells.
The change can happen in two places. Sometimes the vector goes straight into the body, by a drip or an injection into the eye, ear or brain. Other times doctors remove the patient’s own cells, change them in a lab and put them back.

What is a vector, and why use a virus?
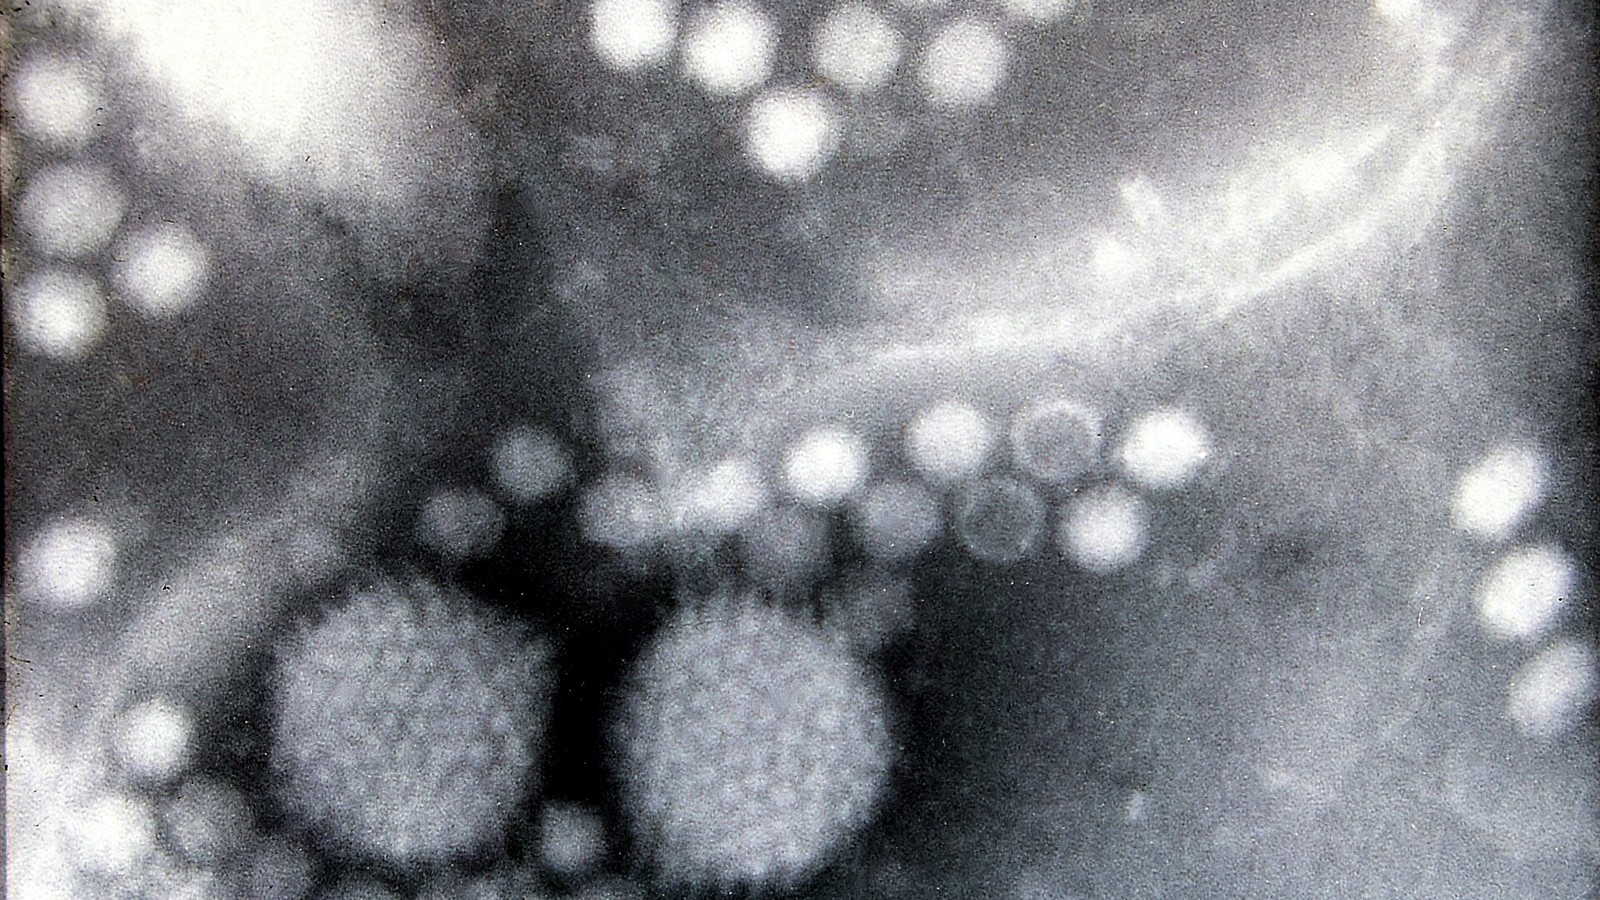
Viruses are very good at getting genetic material into cells. Scientists strip out the parts that make a virus harmful or let it copy itself, then pack in the instructions they want to deliver. Two of these delivery trucks do most of the work today:

- AAV (adeno-associated virus). A small virus not known to cause disease in people (Grokipedia). Its cargo sits beside your own DNA without joining it, which suits cells that rarely divide, like those in the eye, muscle and brain. It can only carry small genes.
- Lentivirus. A virus from the same family as HIV, with the disease-causing parts removed (Grokipedia). It writes its cargo into the cell’s DNA, so the change is passed on when the cell divides. That suits blood stem cells, usually treated outside the body.
The truck can also be told where to unload. A promoter is the switch that decides which cells read the new gene. That was the choice in our story on the AI agent that operated on a mouse: the agent picked an AAV that boosts GABA, the brain’s calming signal, behind a promoter that only works in the brain’s calming nerve cells.
Which gene therapies are approved?
The FDA keeps a running list of approved cell and gene therapy products. A few milestones help show how fast the field has moved:

- December 19, 2017: Luxturna. For an inherited form of vision loss caused by faults in the RPE65 gene. An AAV carries a working copy into cells at the back of the eye (FDA).
- May 24, 2019: Zolgensma. For babies under two with spinal muscular atrophy, which destroys the nerves that control muscles. One drip of AAV delivers a working SMN gene (FDA).
- November 2023: Casgevy, the first CRISPR medicine anywhere. The UK regulator approved it first, for sickle cell disease and the blood disorder beta thalassemia in people aged 12 and over (MHRA).
- December 8, 2023: Casgevy and Lyfgenia in the US. Both treat sickle cell disease. In the trial behind the approval, 29 of 31 Casgevy patients with enough follow-up went at least a year without a severe pain crisis (FDA).
- March 26, 2026: Kresladi. The first gene therapy for a rare immune disorder called severe LAD-I, made from the child’s own modified stem cells (FDA).
- April 2026: Otarmeni. Regeneron’s treatment for deafness caused by OTOF gene faults, injected into the inner ear. In its trial, 16 of 20 children heard better (AABB).
- August and September 2026: Genglycos and Fayuvi. Ultragenyx won approval for a liver disorder called glycogen storage disease type Ia (AABB) and then for Sanfilippo syndrome type A, a fatal childhood brain disease (STAT).
Kresladi, Otarmeni and Genglycos got accelerated approval: they reach patients early, and the companies must still confirm the benefit in further studies.
How is AI speeding up gene therapy?
The hardest part is often the truck, not the cargo. Natural AAVs get swallowed by the liver, miss the tissue you want, or get attacked by the immune system. Changing the capsid shell can fix that, but there are more possible shells than any lab could test. AI narrows the search, much as it does in drug discovery.

- Designing new shells. In a 2021 study, a team from Google Research, Dyno Therapeutics and Harvard used deep learning to design 201,426 versions of one part of the AAV2 capsid. Of those, 110,689 still formed a working shell that could carry DNA (Nature Biotechnology).
- Predicting the shape. Protein structure tools like AlphaFold let researchers check whether a new capsid design will fold correctly before they build it. A February 2026 study, not yet peer reviewed, paired an AI model trained on protein sequences with AlphaFold 3 to design capsids aimed at the kidney (arXiv).
- Choosing the target. AI can read thousands of papers and suggest which gene, cell type and body part to aim for. The mouse experiment above is an early, unreviewed example.
A related approach is being tested in people. uniQure’s AMT-260 uses an AAV to switch off a gene in the hippocampus, a memory area deep in the brain, in people whose temporal lobe epilepsy does not respond to drugs. In June 2026, the company reported that 3 of the first 6 patients had 79% to 100% fewer disabling seizures in months four to six, while the other 3 ranged from a 33% drop to a 36% rise (NeurologyLive). It is early data from six people. Our guide to AI in medicine covers other ways hospitals use AI.

What can go wrong?
A change written into someone’s cells is hard to take back, so safety matters more than usual. The main risks:
- The immune system fights back. The body can treat the vector as an invader. In 1999, 18-year-old Jesse Gelsinger died from a massive immune reaction in an early trial (Grokipedia).
- Liver damage. High doses of AAV travel to the liver. In July 2025 the FDA said three deaths from acute liver failure appeared to be linked to Sarepta’s muscular dystrophy therapy Elevidys and a related experimental therapy using the same AAV type (FDA).
- Cancer risk. Vectors that write into DNA can land in the wrong spot. Blood cancer has occurred in patients treated with Lyfgenia, and its label carries a warning (FDA).
- Tough preparation. Treatments that edit stem cells outside the body, like Casgevy, need high-dose chemotherapy first to clear room in the bone marrow.
Why does gene therapy cost so much?
Casgevy’s US list price is $2.2 million and Lyfgenia’s is $3.1 million (Pharmaphorum). Companies argue that a one-time fix replaces decades of hospital care. Doses are made in small batches, sometimes from one patient’s own cells, and the diseases are rare, so development costs are spread over very few patients.
Insurers and governments are testing new ways to pay. Under a Centers for Medicare & Medicaid Services program for state Medicaid patients with sickle cell disease, the government negotiates discounts and rebates tied to whether the treatment works, and states choose whether to join. Its summary lists 34 participants: 32 states plus Washington, DC and Puerto Rico (CMS).
What is still experimental
Most gene therapy is still in trials. The newest frontier is the one-patient treatment. In 2025, doctors in Philadelphia treated a baby, KJ, with a gene editor built to fix one of his DNA typos, a rare liver disease called CPS1 deficiency. The editor reached his liver inside tiny fat bubbles in place of a virus (GEN). It took months to build, and it is far from a routine treatment.
Open questions remain: how long one dose lasts, whether the approach can reach common diseases, and how safely vectors can reach the brain. We track that work in The Biotech Frontier.
Common questions
How is gene editing different from gene therapy?
Gene editing is one kind of gene therapy. Many approved therapies add a working copy of a gene without changing the original. Editing tools like CRISPR change the DNA where it sits.
Is gene therapy permanent?
It is designed to last a long time, often years, after a single dose. How long it lasts depends on the vector and the cells. Lentiviral changes are copied when cells divide; AAV cargo can fade in cells that divide often.
Can gene therapy change my children’s genes?
Approved treatments change body cells only, not eggs or sperm, so the changes are not passed on to children.
Does AI design gene therapies on its own?
Not for people. AI helps design capsids, predict protein shapes and suggest targets, but scientists test every design in the lab and regulators review every human treatment. The AI agent that chose a therapy for a mouse was a single, unpublished experiment.
Made for regular people, by a real person
A free daily newsletter on what AI is doing in labs, hospitals and everyday life, gene therapy included, explained without the hype. Curated and edited by a human, in plain English.
Free forever. Unsubscribe anytime.
Sources
- NHGRI: Gene therapy (Talking Glossary of Genomic and Genetic Terms)
- FDA: What is gene therapy?
- FDA: Approved cellular and gene therapy products
- FDA: Luxturna (approval letter, December 19, 2017)
- FDA: approval of Zolgensma for spinal muscular atrophy (May 24, 2019)
- MHRA: world-first gene therapy for sickle cell disease and thalassemia (November 16, 2023)
- FDA: first gene therapies for sickle cell disease (December 8, 2023)
- FDA: first gene therapy for severe LAD-I (March 26, 2026)
- AABB: FDA approves first gene therapy for genetic hearing loss (April 2026)
- AABB: FDA approves gene therapy for glycogen storage disease (August 2026)
- STAT: FDA approves a gene therapy for Sanfilippo syndrome (September 2026)
- FDA: Elevidys distribution request and clinical holds (July 18, 2025)
- Pharmaphorum: FDA clears two sickle cell gene therapies, including a CRISPR first (prices)
- CMS: Cell and Gene Therapy Access Model
- Bryant et al.: Deep diversification of an AAV capsid protein by machine learning (Nature Biotechnology, 2021)
- AAVGen: AI-designed AAV capsids for kidney targeting (arXiv preprint, February 2026)
- NeurologyLive: AMT-260 shows early seizure reductions in temporal lobe epilepsy (June 2026)
- GEN: world’s first patient treated with a personalized CRISPR therapy (May 2025)
- Grokipedia: adeno-associated virus
- Grokipedia: lentiviral vectors in gene therapy
- Grokipedia: Jesse Gelsinger